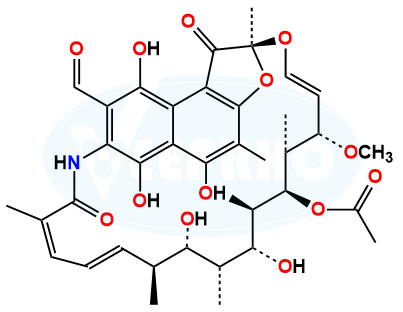
Rifampin, also known as rifampicin, is a broad-spectrum antimicrobial 1 that was first discovered in 1965 2 and clinically used in 1968. 6. It is an ansamycin class antibiotic that exerts bactericidal activity by binding to the beta subunit of the bacterial DNA-dependent RNA polymerase rpoB and blocking transcription initiation; this mechanism confers potent activity against Mycobacterium tuberculosis and other mycobacteria and against many Gram positive organisms and selected Gram negative pathogens when used in combination therapy. Chemically it contains a substituted naphthohydroquinone chromophore linked to an aliphatic ansa chain; the drug is lipophilic with limited aqueous solubility, extensively protein bound, and undergoes hepatic deacetylation to an active metabolite desacetylrifampicin. Rifampin is orally active with variable bioavailability and shows enzyme induction of hepatic cytochromes particularly CYP3A4, which accelerates metabolism of many concomitant drugs and of rifampin itself on repeated dosing through autoinduction, producing a shorter terminal half life during chronic therapy. Clinical use is primarily in combination regimens for tuberculosis, as part of multidrug therapy for certain mycobacterial infections, and for chemoprophylaxis of meningococcal carriage; dosing considerations include drug interactions, hepatic function monitoring, and awareness of characteristic orange discoloration of body fluids.

Parent: Rifampicin
Parent: Rifampicin

Parent: Rifampicin
Parent: Rifampicin

Parent: Rifampicin
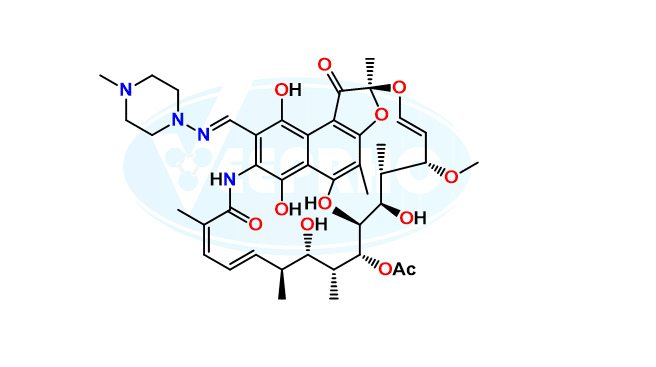
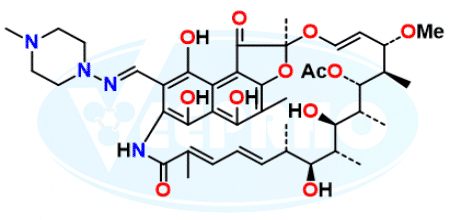
The rifampicin active substance is susceptible to hydrolytic and oxidative degradation that generates a predictable set of related compounds and impurities such as desacetylrifampicin, rifampicin quinone, 3-formylrifamycin derivatives, and other ring-opened or oxidized ansa-chain products; these impurities are monitored in quality control by validated chromatographic methods, typically HPLC with UV detection and LC-MS for structural confirmation. Typical manufacturing and regulatory control strategies specify an assay specification ensuring high potency and limits for impurities to ensure safety and efficacy; specified impurities are commonly controlled at low single-entity levels and the total related substances are limited by monograph or dossier requirements. In practice manufacturers set acceptance criteria informed by pharmacopeial monographs and stability data for example maintaining assay purity generally above about 95 percent w/w and controlling individual known degradants at low percentage levels with total impurities maintained within a few percent, with tighter limits applied to genotoxic or otherwise toxic degradants. Appropriate formulation, storage conditions and antioxidants or pH control during manufacture reduce formation of these related compounds.
Both cetirizine and ebastine are second generation H1 antihistamines with similar indications for allergic rhinitis and chronic urticaria. Cetirizine typically has a rapid onset and is widely used; ebastine has a longer duration of action and is generally considered less sedating in some patients. Choice should be based on individual response, side effect profile, potential drug interactions, patient age and comorbidities rather than a blanket statement that one is superior.
Ebastine is used to treat symptoms of allergic rhinitis and chronic idiopathic urticaria by blocking peripheral H1 receptors, reducing sneezing, nasal itching and rhinorrhea and relieving hives and pruritus.
Ebastine is taken once daily; it can be administered with or without food. For daytime symptom control taking it in the morning is common, while taking it in the evening may help control nighttime symptoms. Follow the prescribing information for specific dosing and consider clinician advice when combining with other central nervous system active drugs.
No, EBASt 10 is not a steroid. It is a brand formulation of ebastine 10 mg, which is a non steroidal antihistamine.